

Ectopic Pregnancy (Tubal Pregnancy) – What Does It Mean and How Does It Present?
An ectopic pregnancy occurs when a fertilised egg implants outside the womb – in a place that cannot support its growth. If an egg remains in such an atypical position, a baby cannot develop from it, and the mother's health may be put at risk if the pregnancy continues.
There are significant risks that can lead to a medical emergency – which is why an ectopic pregnancy must be treated promptly. In this article, you'll find everything you need to know.
What does ectopic pregnancy (extrauterine pregnancy) mean?
A normal pregnancy begins and develops inside the womb (intrauterine) after the egg has been fertilised in the fallopian tube. It then travels to the womb, where it implants within 5–6 days of fertilisation, thereby establishing the pregnancy. Once this happens, the behaviour of the entire reproductive system changes – one of the first signs being a missed period.
So what happens in an ectopic pregnancy? The fertilised egg never reaches the womb and implants elsewhere – a situation that can have serious consequences. The complications of an ectopic pregnancy can endanger the mother's health and even her life.
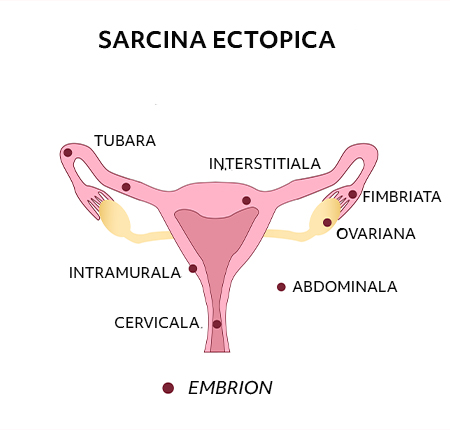
Depending on where implantation occurs, there are several forms of ectopic pregnancy. An ectopic pregnancy can develop:
- in a fallopian tube (tubal pregnancy) – in 90% of cases;
- in an ovary;
- in the cervix (cervical pregnancy);
- in the abdominal cavity.
DID YOU KNOW? Ectopic pregnancies occur in roughly 2% of all pregnancies.
Ectopic pregnancy – symptoms & signs
The first symptoms of an ectopic pregnancy can be very similar to the typical signs of a normal pregnancy. In a separate blog article, we've explained everything about the early signs of pregnancy. You may not notice any symptoms at all to begin with, and a pregnancy test will come back positive. Even so, an ectopic pregnancy cannot continue normally.
When symptoms do appear, they usually develop between weeks 4 and 12 of pregnancy. These may include the following complaints in combination:
- pelvic pain – the pain is often concentrated on one side of the pelvis, namely the side where the pregnancy has implanted;
- pain in the lower back;
- abdominal pain;
- vaginal bleeding or a brownish, watery discharge;
- discomfort when going to the toilet.
With a pregnancy in the fallopian tube, there is a risk of tubal rupture; the symptoms that accompany this are far more severe:
- sudden, intense pain in the pelvis or abdomen;
- shoulder pain – with heavy bleeding, the abdominal and pelvic cavities fill with blood;
- peritonitis (swelling of the abdominal cavity);
- low blood pressure;
- dizziness and even loss of consciousness as a result of significant blood loss.
Any sign that could indicate a rupture in an ectopic pregnancy requires immediate emergency medical care, as the patient's life may be at risk.
How does an ectopic pregnancy happen?
To understand how an ectopic pregnancy comes about, it's first important to know that the ovaries and the womb are connected via the fallopian tubes. For the fertilised egg to reach the womb, it must pass through the fallopian tubes.
In an ectopic pregnancy, the embryo formed after fertilisation usually becomes stuck along its journey through the fallopian tube and never reaches the womb to implant there. Instead, it implants outside the womb or in a scarred, atypical area – and a baby cannot develop from it.
Instead, unusual symptoms appear during the first trimester, and if the pregnancy continues, health problems develop. If you'd like to compare the symptoms of an ectopic pregnancy with those of a normal pregnancy: HERE we've explained in detail how a pregnancy normally develops week by week in each trimester.
At what week is an ectopic pregnancy detected?
An ectopic pregnancy is usually discovered early in pregnancy. Doctors generally diagnose ectopic pregnancies during the first trimester (up to week 12). Most women, however, find out they have an ectopic pregnancy at around the eighth week.
The gestational age at which an ectopic pregnancy is most commonly confirmed is between 6 and 10 weeks. Symptoms usually appear from the fourth week onwards, or 6–8 weeks after the last normal period. A pregnancy calculator can help you work out roughly which week of pregnancy you're in.
Some women notice no unusual symptoms at all early in pregnancy. In that case, they may only learn of the ectopic pregnancy at their first ultrasound scan, when the doctor makes the diagnosis – or only once more serious symptoms appear as the pregnancy progresses without the foetus developing.
As with a normal pregnancy, an ectopic pregnancy is identified through pregnancy tests that measure hCG levels, or through a beta-hCG blood test at a laboratory. HERE we've explained how and when you'll know you're pregnant.
In an ectopic pregnancy, hCG levels rise more slowly, which is why the first readings may be lower – this can lead to a false negative result. Laboratory tests, on the other hand, can detect the hormone hCG considerably earlier, even in an ectopic pregnancy. You can find out HERE which other tests are carried out during pregnancy.
Do you still get your period with an ectopic pregnancy?
Whether or not you get your period with an ectopic pregnancy is a question that concerns many women – and understandably so. Particularly when you consider that if menstruation continues uninterrupted, an important clue is missing, making it far harder to realise you're pregnant. So let's talk about it:
Heavy vaginal bleeding is a sign of an ectopic pregnancy, but it should not be mistaken for a period. Although a pregnancy outside the womb may initially cause no symptoms, menstruation generally stops with an ectopic pregnancy too. So no – you most likely won't get your period.
But as mentioned, heavy bleeding can occur in pregnancy, and this is easily confused with a period. Pay attention to the colour and consistency. Bleeding in an ectopic pregnancy is more watery and lighter, or heavier and darker, than usual menstrual bleeding.
When should you see a doctor?
If you experience sudden, severe pain together with vaginal bleeding, seek medical help immediately. If you notice a combination of the symptoms listed above, you should also speak to a doctor to get your situation assessed.

The longer a medical appointment is put off, the more likely complications become and the higher the risk of death. It's important to know that an early medical examination can prevent complications.
Ectopic pregnancy – causes
There are several possible causes that can lead to an ectopic pregnancy. These include:
- pre-existing inflammation of the fallopian tube
- congenital abnormalities of the fallopian tubes
- long-term use of a coil (IUD)
- hormonal imbalances
- abnormal development of the fertilised egg
- the absence of an ovary
- endometriosis (tissue similar to the womb lining growing outside the womb)
- pelvic inflammatory disease (PID) – inflammation of the female reproductive system, usually caused by a sexually transmitted infection (STI)
- a previous ectopic pregnancy – the risk of another ectopic pregnancy is around 10%
- fertility treatments such as IVF – taking medication to stimulate ovulation (the release of an egg) can increase the risk of an ectopic pregnancy
- smoking
- older age – the risk is highest in pregnant women over 35
Risk factors – ectopic pregnancy
In some patients, the likelihood of an ectopic pregnancy is increased due to certain risk factors. These include existing conditions and medical history, but also harmful habits, such as:
- a previous ectopic pregnancy
- a previous termination of pregnancy
- surgery on the fallopian tubes
- surgery in the pelvic area
- the presence of a coil (IUD) in the womb
- smoking
- being over 35 years of age
- pelvic inflammatory conditions
- appendicitis
- infections (Chlamydia trachomatis)
- sexually transmitted infections
Ectopic pregnancies are not always linked to the presence of risk factors. Around half of all women with an ectopic pregnancy have no risk factors at all.
Complications of an ectopic pregnancy
The reason it's so important to recognise, diagnose and treat an ectopic pregnancy in good time is the potential for serious complications.
An ectopic pregnancy cannot be carried to term, it does not support the baby's development, and survival of the foetus is impossible. Instead, this type of pregnancy endangers the mother's health and even her life.
Because it isn't a normal pregnancy implanted in the womb, it can damage the fallopian tubes and cause heavy bleeding or serious infection. Below you'll find the most common complications of an ectopic pregnancy.
Internal bleeding
Statistics show that most ectopic pregnancies occur in a fallopian tube – this accounts for over 90% of all ectopic pregnancies. As the pregnancy progresses, its growth can cause the fallopian tube to rupture, automatically leading to very severe internal bleeding in the abdomen.
This can happen at any point between weeks 6 and 16, with greater blood loss the later the rupture occurs. Internal bleeding can be life-threatening for the patient. Naturally, the heavier the bleeding, the higher the risk of death. Emergency surgery is required to stop it.
Damage to the fallopian tubes
If an ectopic pregnancy is not identified in good time and no appropriate action is taken, it can cause serious health problems by damaging the fallopian tubes. The main complications are salpingitis (inflammation of the fallopian tubes) or even tubal rupture.
Complications may present as sudden, stabbing abdominal pain, heavy bleeding, dizziness, fainting, pallor and a raised pulse. In severe cases, a tubal rupture can even be life-threatening.
A tubal rupture resulting from an ectopic pregnancy requires emergency treatment. The remains of the pregnancy are removed surgically. Depending on the severity, the ruptured tube may also be removed, or reconstructive surgery may be performed.
Diagnosis – ectopic pregnancy
It's usually difficult to diagnose an ectopic pregnancy from the symptoms alone, as these can resemble other conditions. If you have symptoms of an ectopic pregnancy and a positive pregnancy test, you may be referred to an early pregnancy unit for further investigation.
These investigations include:
- a transvaginal ultrasound scan – for a close-up view of the reproductive system;
- blood tests – to measure the pregnancy hormone; hCG levels are usually lower and rise more slowly than in a normal pregnancy;
- laparoscopic surgery – to examine the womb and fallopian tubes directly.
Can an ectopic pregnancy be seen on an ultrasound scan?
Once pregnancy is confirmed, an ultrasound scan is carried out. This is a non-invasive, radiation-free method that can determine the embryo's location. Your doctor may also arrange a Doppler ultrasound. This increases the chances of detecting an ectopic pregnancy.
Does a pregnancy test detect an ectopic pregnancy?
Since an ectopic pregnancy is initially very similar to an intrauterine pregnancy, a standard pregnancy test will only tell you whether or not you're pregnant. A reliable result can be expected from the first week after a missed period. The urine test commonly used to confirm pregnancy works by detecting hCG (human chorionic gonadotrophin) – the hormone the body produces when a pregnancy is present. Bear in mind, however, that pregnancy tests can also give false results – both negative and positive. Our article explains why a pregnancy test can give a false positive.
It's important to know that a pregnancy test cannot distinguish a normal pregnancy from an ectopic one – regardless of whether hCG is measured in urine or blood. As a rule, such a pregnancy is only discovered once symptoms begin, or even only after a rupture has occurred.
You'll find more useful information about what pregnancy tests are, how to use them and how they work in our article All About Pregnancy Tests.
Ectopic pregnancy – treatment
Sadly, the foetus (the developing embryo) cannot be saved in an ectopic pregnancy. Treatment is usually necessary to end the pregnancy before it progresses too far.
The main treatment options are:
- expectant management – your condition is monitored closely to see whether treatment is needed;
- medication – a drug is used to stop the pregnancy from growing;
- surgery – an operation to remove the pregnancy, usually along with the affected fallopian tube.
Expectant management
If you have no symptoms or only mild ones, and the pregnancy is very small or cannot be located, close monitoring may be sufficient, as there's a good chance the pregnancy will resolve on its own.
This so-called expectant management works roughly as follows:
- You'll have regular blood tests to check whether the hCG level in your blood is falling – these continue until the hormone is no longer detectable.
- Additional treatment will be started if the hormone level does not fall or starts to rise.
- You'll usually experience light vaginal bleeding.
- You may have abdominal pain.
- You'll be told what to do if more severe symptoms develop.
The main advantage of this type of monitoring is that there are no treatment side effects. A disadvantage is that there's still a small risk that one of your fallopian tubes may rupture and that treatment will ultimately be needed after all.
Medical treatment
If an ectopic pregnancy is diagnosed early but expectant management isn't suitable, medical treatment may be recommended. This stops the pregnancy from growing and is given as a single injection into the buttock muscle.

You won't need to stay in hospital after treatment, but you'll have regular blood tests to check whether the treatment is working. Sometimes a second dose is needed, and if it doesn't work, surgery may become necessary.
Surgery for ectopic pregnancy
In most cases, a laparoscopy is carried out to remove the pregnancy before it grows too large.
During a laparoscopy:
- you'll be given a general anaesthetic so that you're asleep throughout the procedure;
- small cuts (incisions) are made in your abdomen;
- a thin viewing instrument (laparoscope) and small surgical instruments are passed through the incisions;
- the entire fallopian tube containing the pregnancy is removed, provided the other tube appears healthy – otherwise, an attempt may be made to remove the pregnancy without sacrificing the whole tube.
Removing the affected fallopian tube is the most effective treatment and does not reduce your chances of becoming pregnant again. Most women can leave hospital a few days after surgery, although full recovery can take 4 to 6 weeks.
If your fallopian tube has already ruptured, you'll need emergency surgery. The surgeon will make a larger incision in your abdomen to stop the bleeding and, where possible, repair the tube.
Psychological support
Recovery after an ectopic pregnancy isn't easy for any woman, and psychological and emotional health needs time to heal too – just as the body does. Losing a pregnancy brings an emotional upheaval that deserves particular attention. If you feel the need, turn to family, friends and, not least, a psychotherapist or psychiatrist who can help you.
Can an ectopic pregnancy resolve on its own?
In a small number of cases, an ectopic pregnancy can resolve on its own – this is when the expectant management described above is used.
Can you get pregnant again after an ectopic pregnancy?
You may want to try for a baby again as soon as you and your partner feel physically and emotionally ready. Is that possible after an ectopic pregnancy?
Your doctor will most likely advise you to wait at least 2 menstrual cycles after treatment before trying again, so your body has time to recover. Most women who have had an ectopic pregnancy are able to conceive again – even if one fallopian tube has been removed. Occasionally, fertility treatment such as IVF may be needed.
The likelihood of another ectopic pregnancy is higher if you've already had one, but the risk remains low. If you do become pregnant again, it's worth telling your doctor as early as possible so that early ultrasound scans can be arranged to make sure everything is as it should be.
Recovery after an ectopic pregnancy
As a rule, a woman can return to her normal activities about a week after laparoscopic surgery to remove an ectopic pregnancy.
During recovery, abdominal pain is normal – which is precisely why it's recommended that you continue taking the painkillers prescribed by your doctor. It's also very important to stay in close contact with your doctor and report any problems that arise.
Diet is another important factor that contributes to a quick, complication-free recovery. Eat light foods such as toast and chicken soup, along with vegetables and fruit that have anti-inflammatory properties. You may have vaginal bleeding for 1 to 4 weeks after surgery.
Prevention – ectopic pregnancy
Although no preventive measure can rule out the risk of an ectopic pregnancy entirely, there are still some steps you can take to reduce the likelihood of this medical problem as far as possible:
- preventing sexually transmitted infections – this includes limiting the number of sexual partners and using a condom during any intercourse not intended for conception;
- stopping smoking before you become pregnant;
- regular check-ups with your gynaecologist to monitor the health of your reproductive system.
Your period after an ectopic pregnancy
Periods after an ectopic pregnancy aren't significantly different from usual. What may surprise you, though, is the vaginal discharge that occurs immediately after the surgery to end the pregnancy.

And because your health matters most, choose ENROUSH pads, made from 100% organic cotton – with no chemical residues, fragrances, chlorine or plastic. Enroush's hypoallergenic, gynaecologically tested organic cotton pads won't cause irritation or allergies, won't upset the pH balance of your intimate area, and give you the confidence you need.
Discover Enroush pads HERE and take your period care to the next level – for you and your health.

Do you get your period with an ectopic pregnancy?
Since an ectopic pregnancy is initially no different symptomatically from an intrauterine pregnancy, your period will stop once you're pregnant. A pregnancy test will let you check whether you're pregnant.
Your sex life after an ectopic pregnancy
Depending on your personal experience, your sex life after an ectopic pregnancy may or may not change. As with any significant, traumatic event, recovery depends very much on how you process it emotionally. Once you feel ready to resume your sex life, do so at your own pace – and accept the difficult moments at the start, because they're part of the process. If you have a normal pregnancy, we've prepared another article for you covering everything worth knowing about sex during pregnancy.
We do have 2 important tips for a healthy sex life:
- limit the number of sexual partners you have
- use condoms – they protect you from both unwanted pregnancy and many sexually transmitted infections
Frequently asked questions
If we haven't answered all your questions yet – perhaps we can now.
When can an ectopic pregnancy be seen on a scan?
By week 12 of pregnancy, your doctor can establish whether or not it's an ectopic pregnancy. An ultrasound scan is usually used for this.
When do you realise you have an ectopic pregnancy?
The symptoms of an intrauterine pregnancy aren't significantly different from those of an ectopic pregnancy. Our advice: see your doctor regularly so that any problem is picked up early, and pay attention to the signals your body is sending you.
What is the beta-hCG level in an ectopic pregnancy?
In a normal pregnancy, serum beta-hCG levels double every 48–72 hours until a level of 10,000–20,000 mIU/mL is reached. In an ectopic pregnancy, serum beta-hCG rises more slowly, so the values are lower than in a normal pregnancy.
A single reading does not prove an ectopic pregnancy. Careful medical assessment is required.
How long does an ectopic pregnancy last?
As a rule, a doctor will determine in the first months of pregnancy whether it is intrauterine or ectopic. Since only the womb can nourish a baby and allow it to grow, an ectopic pregnancy will not survive and must be ended surgically or with medication.
Why is an ectopic pregnancy dangerous?
An ectopic pregnancy, which in over 90% of cases is implanted in the fallopian tubes, does not allow the foetus to develop or survive. The baby cannot be nourished or grow outside the womb. Instead, the growth of the pregnancy can lead to serious complications such as tubal rupture and massive internal bleeding, which can even endanger the mother's life.
Sources used:
- NIH, 'Risk factors and clinical characteristics associated with a ruptured ectopic pregnancy': https://www.ncbi.nlm.nih.gov/pmc/articles/PMC9276220/
- NIH, 'Ectopic Pregnancy': https://www.ncbi.nlm.nih.gov/books/NBK539860/
- Ada, 'Ectopic Pregnancy': https://ada.com/conditions/ectopic-pregnancy/
- NHS, 'Ectopic Pregnancy': https://www.nhs.uk/conditions/ectopic-pregnancy/
- WebMD, 'Ectopic Pregnancy: What To Know': https://www.webmd.com/baby/pregnancy-ectopic-pregnancy
- Cleveland Clinic, 'Ectopic Pregnancy': https://my.clevelandclinic.org/health/diseases/9687-ectopic-pregnancy
- American Journal of Obstetrics & Gynecology, 'Ectopic pregnancy not within the (distal) fallopian tube: etiology, diagnosis, and treatment': https://www.ajog.org/article/S0002-9378(11)02162-4/fulltext
- UCDavisHealth, '7 things to know about ectopic pregnancy': https://health.ucdavis.edu/news/headlines/7-things-to-know-about-ectopic-pregnancy/2022/05

Medium, super or extra absorption

Low, medium or super absorption

Low or medium absorption


and happily breaking taboos!


